
 If you care for someone with dementia, it’s almost certain you’re also managing other health conditions. Research shows more than 86% of people living with dementia have at least one other chronic condition alongside it, and roughly three-quarters have three or more PMC (PubMed Central). High blood pressure, diabetes, heart disease, arthritis, depression, and COPD are the most common. The good news: with the right systems, the right questions, and a coordinated care team, families can manage this complexity at home with better quality of life for everyone.
This guide explains exactly what comorbidities mean in dementia care, which conditions matter most, why they complicate daily life, and how you can build a practical at-home care routine plus the red flags that warrant an immediate call to a doctor.
What Are Comorbidities in Dementia?
A comorbidity is simply a second (or third, or fourth) chronic health condition that exists alongside the primary diagnosis. In dementia care, comorbidities are the rule, not the exception.
- >86% of people with dementia have multimorbidity (two or more chronic conditions) PMC (PubMed Central)
- In one study of nearly 150,000 primary care patients, 86.7% of people with dementia had at least two other conditions (vs. 63.9% of matched controls), and 74.8% had three or more (vs. 53% of controls) PMC (PubMed Central)
- People with dementia average four coexisting conditions PMC (PubMed Central)
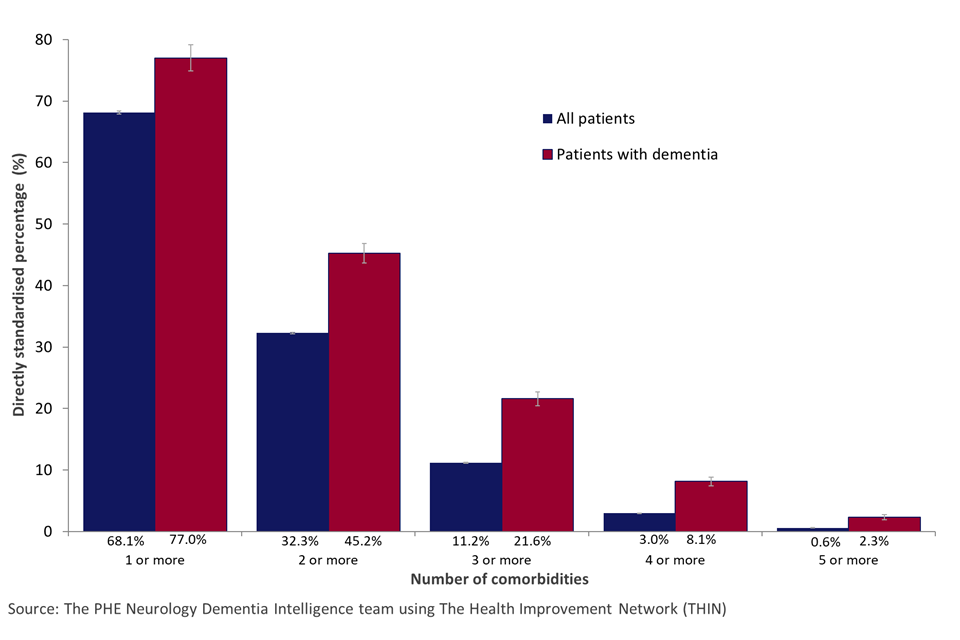
- A UK national data briefing found 77% of dementia patients have at least one of the studied comorbidities, 22% have three or more, and 8% have four or more (vs. 11% and 3% in the general patient population) GOV.UK
Which Health Conditions Most Commonly Occur With Dementia?
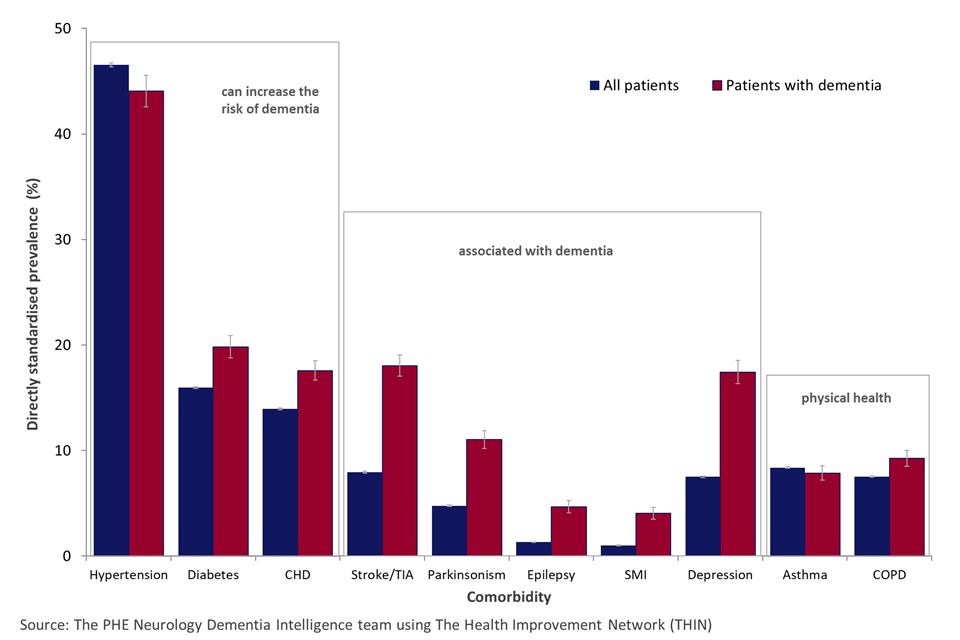
These figures come from the same UK primary-care data briefing covering roughly 100,000 records — and they mirror findings worldwide GOV.UK:
| Condition found with dementia | Rough prevalence | Why it matters at home |
|---|---|---|
| High blood pressure (hypertension) | ~44% | Most common comorbidity; good control supports brain and heart health, but overtreating can cause dizziness and falls |
| Diabetes | ~17–20% | Low or high blood sugar can mimic or worsen confusion; missed meals and forgetting insulin are real risks |
| Stroke or TIA | ~17–20% | Shared vascular burden; medication adherence and swallow-safety become priorities |
| Heart disease (CHD) | ~17–20% | Chest pain may go unreported; watch for breathing changes or sudden fatigue |
| Depression | ~17–20% | Easy to confuse with dementia apathy; treating it measurably improves quality of life |
| Parkinsonism | ~11% | Gait changes, freezing, fall risk, and swallowing difficulties |
| COPD or asthma | ~9–11% | Breathlessness fuels anxiety and agitation; pacing and positioning help |
| Epilepsy | ~5% | Seizure safety and medication monitoring |
| Severe mental illness | ~4% | Complex medication regimes need extra coordination |
Important caveat: these numbers likely underestimate reality. Diagnosis of coexisting conditions becomes more difficult as dementia severity increases, so many comorbidities go unrecognized — meaning unmet health needs. If your loved one hasn’t had a recent, thorough medical review, that’s the place to start GOV.UK.
Why Do Comorbidities Make Dementia Care So Much Harder?
1. Symptoms don’t look the same
People with dementia often can’t report symptoms the way you or I would. Instead of “I have a burning feeling when I pee,” a urinary tract infection (UTI) may show up as sudden confusion, drowsiness, falls, and incontinence, or a dramatic worsening of behavior PMC (PubMed Central). UTIs are one of the most common triggers of delirium — a sudden, fluctuating, severe confusion state that is a medical emergency and can worsen the underlying dementia Cedars-Sinai, Alzheimer’s Society UK.
2. Pain is masked — and it shows up as behavior
People in advanced dementia have a diminished capacity to communicate discomfort, so untreated pain is frequently expressed as behavioral and psychiatric symptoms PMC (PubMed Central). Research links pain strongly to agitation, aggression, and depression across all dementia subtypes. Screaming, cursing, striking out, or sudden withdrawal may all be pain talking Mayo Clinic Health System. When behavior changes, ask “what hurts?” before assuming it’s “the dementia.”
3. Medications pile up — and some make dementia worse
Multiple conditions mean multiple prescriptions, and polypharmacy is a major contributor to anticholinergic burden, which is linked to cognitive and physical decline, falls, and hospitalisation PMC (PubMed Central). The stakes are real:
- Taking an anticholinergic medication (common in allergy, bladder, sleep, and depression drugs) for the equivalent of three years or more was associated with a 54% higher dementia risk L.A. Care Health Plan
- A “severe” anticholinergic burden has been linked to a 227% increased risk of developing cognitive impairment bpacnz
4. Falls become a constant risk
Dementia roughly doubles fall risk — some estimates suggest as many as 80% of dementia patients fall at least once a year PMC (PubMed Central). Nationally representative US data found 45.5% of older adults with dementia had one or more falls in a single year Drexel University. In Canada, 15.9% of hospital admissions among seniors with dementia are fall-related, versus 7.4% among seniors without dementia CIHI. Each fall also carries its own cascade of complications — fractures, hospital delirium, loss of mobility and confidence.
How to Manage Dementia + Comorbidities at Home: A Carer’s Guide
1. Build one care team — and one point of contact
Complex care needs a conductor. Designate one family member to coordinate appointments, and ask the primary care doctor to act as the hub. Research is clear that comprehensive dementia care requires a partnership between doctors, health care workers, and families, with a coordinated plan rather than siloed specialists PMC (PubMed Central). Integrated care models that combine medical, social, and community resources — with a skilled coordinator overseeing both dementia and coexisting conditions — consistently reduce hospitalizations and emergency visits PMC (PubMed Central).
2. Do a “brown bag” medication review
At least once a year — and every time a drug is added or stopped — put every medicine (prescription, over-the-counter, supplements) in a bag and take it to the pharmacist or doctor. Ask:
- Which of these are anticholinergic? (Bladder-control, allergy, and some sleep medications frequently are.)
- Is there a drug with a lower-risk alternative we could try?
- Can any medicine be deprescribed — tapered or stopped under supervision?
Deprescribing is increasingly shown to be feasible, safe, and to improve health outcomes PMC (PubMed Central), but it must be done with the prescribing clinician — never by simply stopping pills at home. Pharmacy-level reviews can catch interactions that no single specialist sees.
3. Keep a behavior and symptom log
Because people with dementia can’t always tell you what’s wrong, an outsider’s observations become the medical record. Keep a simple daily log noting: sleep quality, appetite and fluids, bowel habits, mood and behavior changes, pain cues (grimacing, guarding, moaning, striking out), and what was different that day (new food, new med, missed dose). Bring it to every appointment — it’s the single most valuable tool for a doctor who sees your loved one for ten minutes. Care professionals generally agree that most behavioral expressions are attempts to communicate something — discomfort, fear, or overwhelm UCSF Memory and Aging Center.
4. Fall-proof the home
With comorbid conditions like diabetes, heart disease, and Parkinsonism layered onto dementia, fall prevention is not optional. Practical steps: remove trip hazards and loose rugs, install grab bars in bathroom and beside the bed, improve lighting (especially night lights), secure or remove wheeled furniture, and ask about a mobility assessment. Keep consistency in routines — bathing, dressing, and eating at the same times each day reduces restlessness and confusion Alzheimer’s.gov.
5. Plan ahead — early, not late
Palliative care isn’t just end-of-life care; it’s comfort and quality-of-life care available from diagnosis onward, focused on managing pain and distressing symptoms while supporting the family Alzheimer Society of Canada, NHS. Have the conversations about values, treatment preferences, and who holds medical power of attorney while your loved one can still participate. A proactive plan prevents rushed decisions in a crisis.
6. Care for the Carer
Carer strain is a documented health crisis of its own:
- About 40% of family carers of people with dementia experience depression, versus 5–17% of non-care givers of similar age Caregiver Action Network
- 60% report high or very high stress levels BrainCheck
- 70% say coordinating care is stressful Alzheimer’s Association
In the US alone, 11.5 million family and other care workers provided care to people with Alzheimer’s or other dementias in 2023 Alzheimer’s Association. Use respite care, join a carer’s support group, accept help when it’s offered, and treat your own rest as part of the care plan — a depleted carer cannot keep anyone safe.
Red Flags: When to Call a Doctor Immediately
| Sudden change | Possible cause | Action |
|---|---|---|
| New or sharply worse confusion within hours/days | Delirium (often UTI, dehydration, infection, or medication change) | Call doctor or 111 now |
| Fever, shaking, or chills | Infection | Call doctor now |
| New moaning, grimacing, striking out, or withdrawal | Untreated pain | Call doctor; request a pain assessment |
| Fall with a hit to the head | Head injury, bleeding | Emergency care |
| Chest pain, severe breathlessness, or new weakness on one side | Heart or stroke symptoms | Call 999 |
| Very low or very high blood sugar symptoms (sweating, shaking, confusion) | Diabetes crisis | Follow diabetes care plan; call doctor |
When in doubt, call. “It’s probably just the dementia” is exactly how UTIs and silent heart problems go undetected, and unexpected reversible causes of confusion are found every day
Frequently Asked Questions
Q: What are the most common comorbidities in people with dementia? Hypertension leads the list at about 44%, followed by diabetes, stroke or TIA, heart disease, and depression (each roughly 17–20%), then Parkinsonism, COPD/asthma (around 9–11%), epilepsy, and severe mental illness. In total, more than 86% of people with dementia live with at least one other chronic condition GOV.UK, PMC (PubMed Central).
Q: Why does a person with dementia suddenly become more confused? Sudden confusion that comes on over hours or days — especially with drowsiness, falls, or a change in behavior — is usually delirium, not the dementia progressing. Common triggers are urinary tract infections, dehydration, infections, and new medications. Delirium is a medical emergency and needs prompt evaluation Alzheimer’s Society UK.
Q: Can a urinary tract infection make dementia symptoms worse? Yes — UTIs are one of the most common causes of sudden, severe confusion in people with dementia, and repeated episodes can worsen the underlying condition. UTIs in this age group often present atypically: confusion, dizziness, drowsiness, falls, and incontinence rather than burning or fever PMC (PubMed Central), Cedars-Sinai.
Q: Is untreated pain a cause of agitation in dementia? Very often, yes. Because communication declines, pain is frequently expressed through agitation, aggression, crying out, or withdrawal. Treating pain — including arthritis pain, constipation, and dental issues — often reduces these behaviors more effectively than behavioral medications PMC (PubMed Central), Mayo Clinic Health System.
Q: How many medications is too many for someone with dementia? There’s no single “safe number,” but the more medicines — especially those with anticholinergic effects (common in bladder, allergy, and sleep drugs) — the higher the risk of confusion, falls, and faster cognitive decline PMC (PubMed Central). Ask for a structured medication review at least yearly and consider deprescribing with your prescriber’s guidance PMC (PubMed Central).
Q: Can treating high blood pressure and diabetes help someone with dementia? Managing vascular risk factors matters to brain health. The 2024 Lancet Commission on Dementia positions hypertension, hearing loss, diabetes, and depression as modifiable risk factors across the life course — a reminder that good control of coexisting conditions supports cognitive health as well as overall wellbeing PMC (PubMed Central).
Key Takeaways
- Dementia often exists alongside other long-term health conditions: 86%+ of people with dementia have other chronic conditions; the average is four. PMC (PubMed Central)
- Behaviour is communication — agitation, aggression, and withdrawal are often untreated pain, infection, or discomfort
- A sudden change in confusion may indicate an underlying health problem — such as delirium, a UTI, dehydration or a reaction to medication — and should not automatically be attributed to dementia.
- Regular medication reviews are important, particularly where a person is taking several medicines or medications that may affect memory, alertness or thinking.
- Reducing the risk of falls is a key part of safe dementia care — dementia can increase the likelihood of falls and related hospital admissions. CIHI
- Carer wellbeing is an important part of dementia care — caring for someone with dementia can be emotionally and physically demanding, so access to respite, practical support and time to recharge is important. Caregiver Action Network
- Early care planning helps ensure a person’s wishes are understood — including preferences around future treatment, palliative care and who they would like involved in important decisions.
This article is for educational purposes and is not medical advice. Always consult your loved one’s physician, pharmacist, or other qualified healthcare provider about their specific conditions, medications, and symptoms.